Design Pattern · Sep 10, 2026
Month-End Is an Evidence Problem
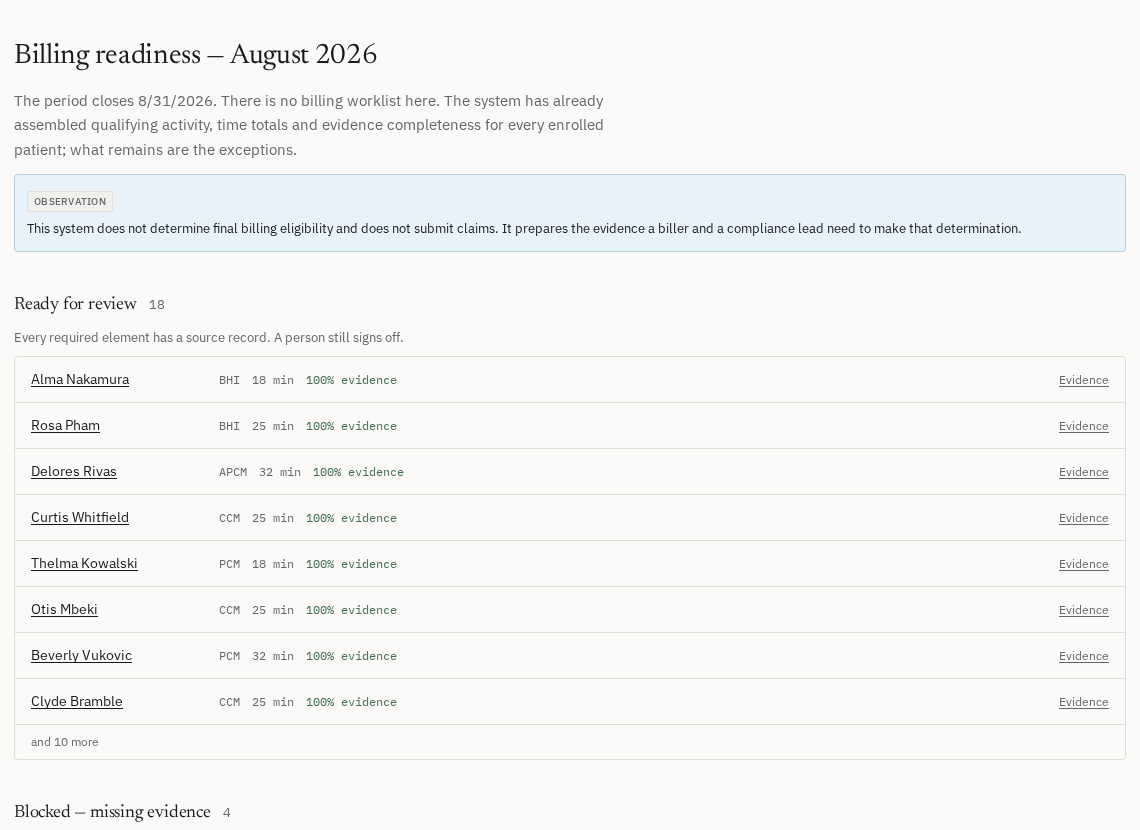
Billing readiness presented exception-first: what is ready, what is blocked and why, what conflicts with policy, and what is documented but should not be billed. The system never asserts final eligibility and never submits a claim.
Under the pillar Zero Dashboard Experiences
Thesis
Month-end close is not a billing task with a documentation problem attached. It is an evidence task whose output happens to be billable.
The argument
The conventional month-end is a worklist worked under time pressure, in which evidence is assembled retrospectively from memory. That process reliably produces two failures at once: care that was delivered and cannot be substantiated, and time that is recorded because the threshold required it.
The alternative assembles evidence continuously and presents only the exceptions at close, in categories that map to who resolves them: ready for review, blocked on missing evidence, policy conflict, needs coding judgment, and documented but not billable.
The last category is the one that signals seriousness. Recording clinically relevant, non-billable work rather than deleting it means the organization can see the difference between care delivered and care reimbursed. Under a system that only tracks billables, that gap is invisible by construction.
The standing constraint sits on the page itself: this system does not determine final eligibility and does not submit claims. It prepares the evidence a biller and a compliance lead need in order to decide.
What a legacy vendor would say
That billing rules change constantly and a system that reasons about them will be wrong in ways a rules engine is not; that surfacing non-billable documented work invites an auditor to ask why it was performed; and that customers judge these products on captured revenue, not on evidence quality.
The revenue objection explains the market. A product measured on capture rate has an incentive to resolve ambiguity in the direction of billing, which is precisely the incentive this pattern refuses.
What would settle it
Audit outcomes over several cycles: denial rate, clawback rate, and the proportion of records where the evidence supported the claim on independent review. A close process that captures more and survives audit worse has lost.
Open questions
Whether exception categories generalize across program mixes or need to be organization-specific. How to handle a genuinely ambiguous coding boundary without either forcing a decision or letting the record sit open. Whether making non-billable care visible changes how much of it gets delivered.
Put this to work
Month-End Is an Evidence Problem application record
Apply Month-End Is an Evidence Problem to a real piece of work and record what happened.
- For
- Clinical, operational, product, reimbursement, and implementation leaders.
- What you keep
- A month-end is an evidence problem application record you can review, revise, and send.
- What counts as sound
- Names a real setting
- Shows the work before and after
- Records exceptions
- Uses an observable result
- Ends with keep, revise, or stop
Clinical, regulatory, privacy, and release decisions remain with qualified people.
Nothing entered here is stored or sent. Review the prompt before sharing confidential, personal, patient, or privileged information.
Review the prompt
You can leave any field blank. The prompt will mark it as not provided.
If the record survives your review, send the question, evidence, unknowns, and requested next step.