Design Pattern · Sep 10, 2026
Populations Without Tables
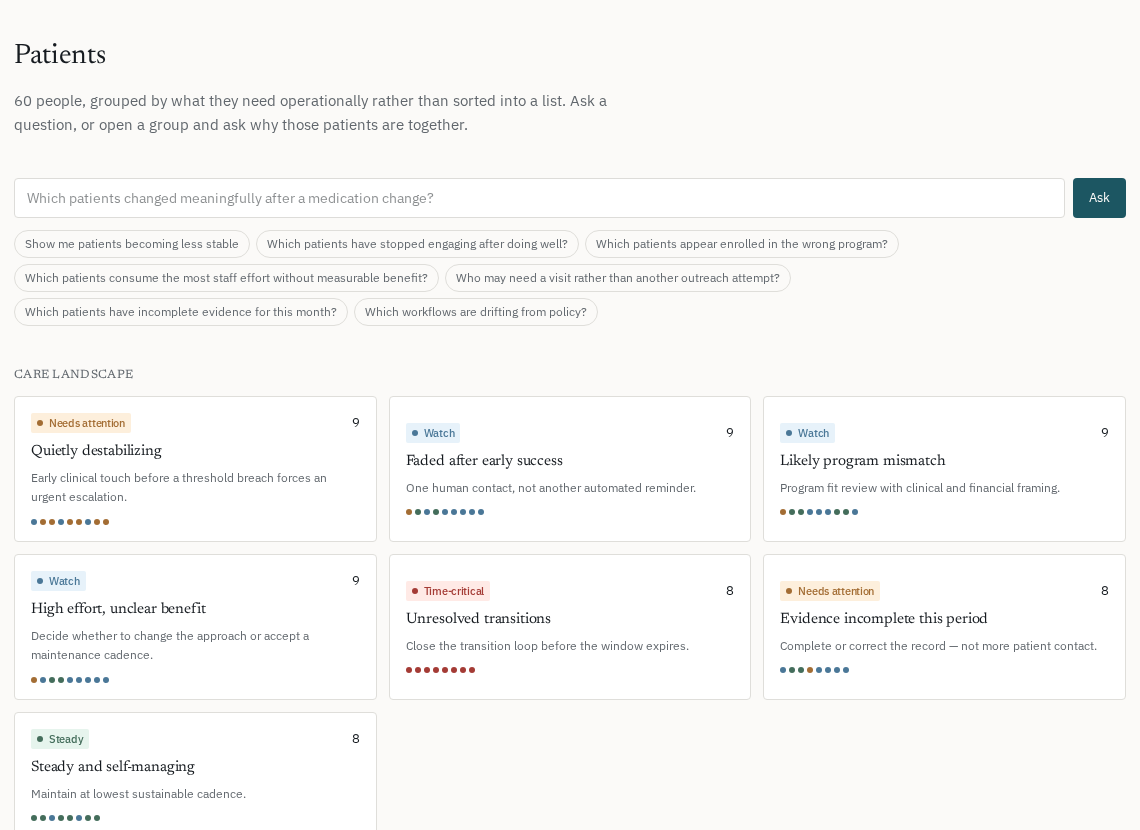
Clustered groups of patients and a conversational explorer replace the filter-and-sort grid. Patients are grouped by what they need operationally, and the grouping itself can be interrogated.
Under the pillar Zero Dashboard Experiences
Thesis
A patient table is a tool for a person who must construct the population themselves. When the system can construct it, the interface should present groups with reasons and answer questions about them.
The argument
Filter-and-sort assumes the operator already knows which attribute predicts the work. The useful groupings are usually not attributes at all: patients quietly destabilizing without breaching a threshold; patients who faded after early success; patients whose program looks like a mismatch; patients absorbing effort with no measurable benefit; patients whose evidence is incomplete this period. None of these is a column.
The pattern has two halves. A cluster view shows the operational groups with a count, a posture, and a one-line statement of what the group needs. An ask box takes a question in plain language and answers it against the population, with the reasoning available.
A cluster has to be able to say why it exists. A group whose membership cannot be explained is a black box with a friendly label, which is worse than a filter because it looks like understanding.
The alphabetical roster still exists. It is treated as a utility, not as the way work is found.
What a legacy vendor would say
That clinical staff need to find a specific patient quickly and a grid does that reliably; that clusters generated by a model are unstable between periods; and that a conversational surface makes work impossible to standardize, audit or train.
Instability is the real risk. A cluster that reshuffles weekly cannot anchor an operating rhythm, and staff will build their own shadow lists rather than trust it.
What would settle it
Cluster stability measured directly: what proportion of members persist between periods, and whether departures are explainable. Then a task study of find-the-population work, timed against a grid, including the tasks a grid cannot express at all.
Open questions
Whether operational clusters should be model-derived, policy-defined, or a fixed vocabulary the model assigns into. How to expose a question's own uncertainty when the answer is a set of people. Whether staff who navigate by cluster keep an accurate mental model of the patients in no cluster at all.
Put this to work
Populations Without Tables application record
Apply Populations Without Tables to a real piece of work and record what happened.
- For
- Clinical, operational, product, reimbursement, and implementation leaders.
- What you keep
- A populations without tables application record you can review, revise, and send.
- What counts as sound
- Names a real setting
- Shows the work before and after
- Records exceptions
- Uses an observable result
- Ends with keep, revise, or stop
Clinical, regulatory, privacy, and release decisions remain with qualified people.
Nothing entered here is stored or sent. Review the prompt before sharing confidential, personal, patient, or privileged information.
Review the prompt
You can leave any field blank. The prompt will mark it as not provided.
If the record survives your review, send the question, evidence, unknowns, and requested next step.